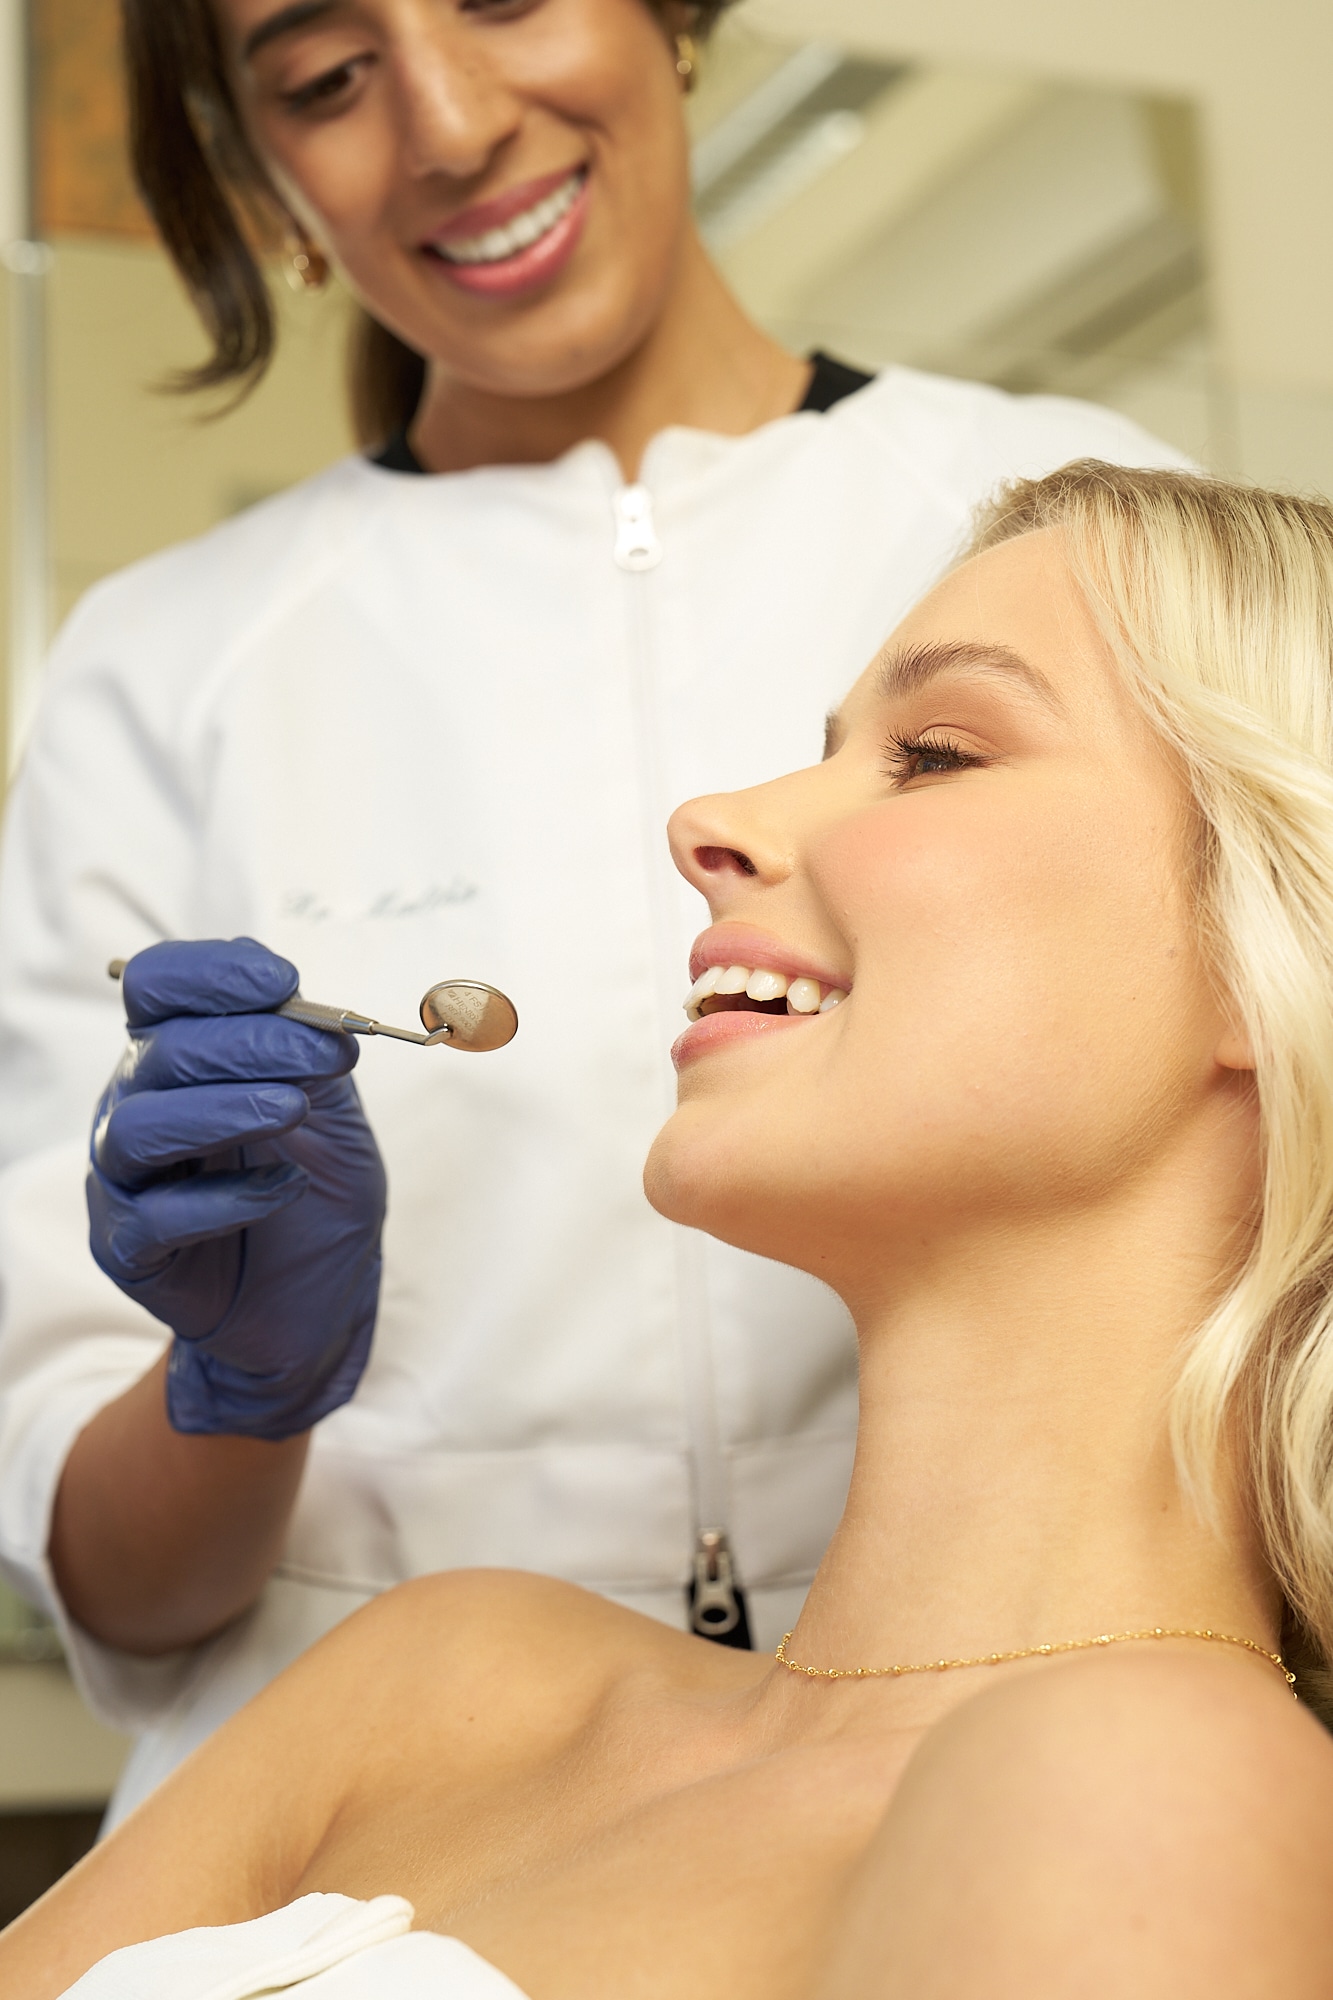
Dental Cleans and Hygienists
Why do I need a hygienist if I already brush and floss?
Because of calculus — tartar — and the fact that brushing and flossing cannot remove it.
Over time, calculus builds up on the teeth both above and below the gum line, in the natural pockets surrounding each tooth. Once plaque hardens into calculus it is mechanically bonded to the tooth, and no home routine will shift it. That requires professional instruments.
Left untreated — especially below the gum line — calculus contributes to gingivitis (gum inflammation) and, in susceptible people, to periodontitis (advanced gum disease involving bone loss).
Many dental diseases are largely preventable, which is the whole argument for a regular hygiene appointment.
Smile Solutions is at Level 1, 220 Collins Street, Manchester Unity Building, Melbourne CBD.
Why calculus matters more than it looks
The visible deposit behind the lower front teeth is the part people notice, and it is the least important part.
Calculus is porous and permanently colonised by bacteria. It cannot be sterilised and it cannot be brushed clean, so wherever it sits it holds a bacterial layer against the gum continuously. Above the gum that produces inflammation; below the gum, in the crevice around each tooth, it keeps that inflammation going in exactly the place where the bone supporting the tooth can be lost.
That is why a clean is not a cosmetic appointment. Removing calculus removes the surface the disease lives on, and it is the single thing home care cannot do.
What a dental hygienist actually does
Hygienists are trained clinicians who specialise in maintaining gum health and preventing decay and erosion. Hygiene is its own discipline, not a simplified version of dentistry.
They typically hold an Advanced Diploma or Bachelor of Oral Health, and are registered with the Dental Board of Australia through AHPRA in their own right.
Their work covers:
- professional cleaning
- evaluating the condition of teeth and gums
- building a tailored care plan with you
- demonstrating correct brushing and flossing technique
- detailed instruction for your home routine
That last part matters more than it sounds. Most people brush with a technique nobody ever corrected, and a hygienist watching you do it is one of the few opportunities to fix that.
What happens in a hygiene appointment
1. Initial assessment. Your hygienist evaluates your overall dental health, gums and teeth, addresses any concerns you raise, and explains their findings — including whether your current home routine is sufficient or whether additional treatment is needed.
2. Routine clean. Teeth are professionally cleaned to remove plaque and bacteria. Hardened calculus is removed first with an ultrasonic device, which gently knocks it off while flushing the gums with water to clear bacteria.
3. Fine cleaning with hand instruments. The detail work the ultrasonic device cannot do, particularly below the gum line.
4. Polishing. Once all calculus is removed, teeth are polished with a handpiece and polishing paste. This smooths the surfaces — which matters practically, because plaque adheres more readily to rough surfaces.
5. Fluoride treatment. After rinsing, fluoride is applied to strengthen the teeth and protect against decay.
The numbers behind the appointment
A thorough hygiene visit produces a record, not just a clean mouth. What gets measured:
- Pocket depths. A fine graduated probe measures the crevice around each tooth at several points. One to three millimetres is healthy; four and above means the attachment has been lost and the pocket can no longer be cleaned at home.
- Bleeding on probing. Recorded as a percentage of sites. This is the metric that actually tracks inflammation, and it is the one that responds fastest to a change in your home routine.
- Recession — how far the gum has moved down the root, which combined with pocket depth gives the true attachment level.
- Mobility, and furcation involvement where the roots of a molar divide.
- A plaque score, which shows where you are missing, in a way no general advice can.
Ask for your numbers. They are the difference between “your gums look a bit inflamed” and a baseline you can actually be measured against next visit, and improvement in a bleeding score is the clearest evidence that something you changed at home is working. See Bleeding Gums.
A clean is not the same as gum treatment
These two appointments share instruments and nothing else, and the distinction is worth insisting on.
A scale and clean is a preventive appointment for someone whose gums are essentially healthy: remove the deposits, polish, fluoride, review technique, rebook in six months.
Periodontal therapy — root surface debridement — is the treatment of established disease. It works on pockets deep enough that instruments have to reach well below the gum, it is usually done under local anaesthetic, often one quadrant of the mouth at a time, and it is followed by a re-assessment around six to eight weeks later to measure whether the pockets have responded.
If you have been told you have pockets and then booked in for a routine clean, ask which of the two you are actually having. A standard clean will not resolve established periodontitis, and repeating it every six months while the disease progresses is the most common way gum disease is missed. Advanced cases are referred to a specialist periodontist.
What a clean can and cannot do about stains
Worth setting expectations, because this is where disappointment usually comes from.
A clean removes stain that is on the tooth — tea, coffee, red wine, smoking, some mouthwashes, curry. Teeth often look noticeably brighter afterwards, and that is the calculus and surface stain coming off, not a colour change.
It does not change the colour of the tooth itself. Discolouration within the enamel and dentine — from age, from a knock, from tetracycline exposure in childhood — is unaffected by any amount of polishing. Changing that is teeth whitening, which is a different treatment altogether.
It also does not change the colour of fillings, crowns or veneers. Restorations do not lighten, which is why any whitening plan is discussed before new front-tooth work rather than after.
What to expect afterwards
A clean is not usually uncomfortable, but it is honest to say what can happen:
- Some sensitivity to cold for a few days is common, particularly if there was heavy calculus below the gum line or if your gums have receded.
- Gums may bleed a little during and after, especially if they were already inflamed. That settles as the inflammation resolves.
- Where deposits were filling a gap, removing them can leave a space that feels larger. The space was already there; the calculus was occupying it.
- Avoid strongly staining food and drink for the rest of the day after a polish or Airflow — the surface takes up colour more readily for a short time.
- If you have had a joint replacement, heart valve surgery or endocarditis, or you take anticoagulants, tell your clinician — it may change how the appointment is managed.
Tell your hygienist if any part of it hurts. Cleans can be done in stages, or with local anaesthetic, if that makes them manageable. If it is the appointment itself rather than the discomfort, see Dental Anxiety.
Airflow technology
We use Airflow, a gentle, non-invasive cleaning system combining air, warm water and fine powder to remove plaque, stains and bacteria.
Many patients find it more comfortable than traditional scaling, which is relevant for anyone who has avoided cleans because of sensitivity or dislike of the scraping. It supplements rather than replaces scaling — hardened calculus below the gum line still needs instruments.
Tell your clinician if you have a respiratory condition, are on a salt-restricted diet, or are pregnant; powder choice and technique are adjusted accordingly, and that is a conversation to have before the appointment rather than during it.
Cleans are performed by experienced Oral Health Therapists who dedicate the entire appointment to hygiene care, rather than fitting a clean around other treatment.
Smile Solutions' hygiene department has been operating since 1993.
Hygienist, dentist or periodontist?
These three roles are frequently confused, and knowing which one you need saves time.
| Role and focus | When to visit | |
|---|---|---|
| Dental Hygienist | Professional cleans and gum health monitoring; assessment and prevention of future problems | Routine cleaning and gum check-ups, at the interval your clinician recommends |
| General Dentist | Check-ups and general dental health | Cavities, fillings and general concerns |
| Specialist Periodontist | Prevention, diagnosis and treatment of gum disease; also dental implants, bone grafts and gum lifts | When referred by a dentist or hygienist for advanced gum issues or implants |
For patients with more advanced gum concerns, Smile Solutions' senior periodontist team provides specialist care in the same building — so escalation from hygienist to periodontist is internal. Specialist Periodontists.
How often, really?
Six months is the common default, and it suits most people. It is not a rule that fits everyone.
Patients with periodontitis, heavy calculus formation, diabetes, a dry mouth, orthodontic appliances or implants are often advised to come every three or four months, because the interval that keeps the disease stable is shorter. Others with low risk may safely go longer.
Why three months, specifically? After a thorough clean, the bacterial community in the pockets begins re-establishing within weeks and is substantially back by around three months. For someone with healthy gums that does not matter. For someone whose attachment has already been lost, it is the point at which the disease starts moving again — so the recall interval is set to arrive before it does.
The right interval for you is a clinical judgement made after assessment, and it can change over time. Ask what yours is and why.
If you have implants, braces or aligners
Implants need their own maintenance regime. The tissue around an implant has no periodontal ligament and a different blood supply, so inflammation there behaves differently and can progress to bone loss around the implant. Cleaning is done with instruments chosen not to scratch the implant surface, and the recall interval is usually shorter. See Dental Implants.
Fixed braces trap plaque around every bracket, and the classic consequence is white demineralised marks left behind when the brackets come off. Cleans during orthodontic treatment are preventive, not optional. See Orthodontic Braces.
Clear aligners cover the teeth for most of the day, which means anything on them stays against the enamel. Brush before re-inserting, and keep the aligners themselves clean.
During pregnancy, hormonal changes make gums more reactive to the same amount of plaque, and bleeding often increases even where nothing else has changed. Dental cleans during pregnancy are routine; tell your clinician which trimester you are in.
If you smoke, one point is worth knowing: smoking suppresses gum bleeding while making the disease worse. The warning sign most people rely on is the one that stops appearing, which is exactly why measurements matter more than symptoms.
Between appointments
1. Brush twice a day. Morning and night, approximately two minutes, using a gentle circular motion or an electric toothbrush.
Two details change the result more than any product: angle the bristles towards the gum line at about forty-five degrees, because that junction is where inflammation starts; and with an electric brush, guide it slowly tooth by tooth rather than scrubbing — the brush is already doing the movement.
Spit, do not rinse. Rinsing straight after brushing washes away the fluoride before it can work.
2. Floss daily. A gentle sawing motion reaching just below the gum line — without damaging the gums. Interdental brushes such as Piksters can reach areas a toothbrush cannot, and where the space is wide enough to take one, an interdental brush removes more plaque than floss. Sizing is the part people get wrong; ask your hygienist to size them for you.
3. Maintain a healthy diet. Balanced meals low in sugar and acid, and limit snacking — frequency of exposure matters as much as quantity.
4. Schedule regular check-ups, so problems are prevented or caught early.
5. Replace the brush head every three months, and sooner once the bristles splay.
What else the appointment picks up
A hygiene visit is often the most frequent contact anyone has with a clinician, and it doubles as a screening appointment. Alongside the gums, your clinician looks at the soft tissues — cheeks, tongue, floor of the mouth, palate and throat — for anything that has changed.
Anything that has not healed in two weeks — an ulcer, a red or white patch, a lump, a persistently sore area — should be reported rather than waited out. Most are harmless; the point of looking is that the ones that are not are far more treatable when found early.
Cleans also frequently pick up worn or chipped restorations, cracks, food packing between teeth, early decay, and appliances that no longer fit — which is why the hygienist is often the first person to raise something the dentist then treats. See Tooth Fillings and Bad Breath.
Cover
We are a Bupa Members First Platinum provider. Eligible Bupa Platinum members with hospital cover combined with extras including general dental may receive a 100% rebate on certain preventative services — check-ups, scale and cleans, examinations, consultations, bitewing x-rays and fluoride treatments among them.
Eligibility, annual limits, waiting periods and policy restrictions are set by Bupa and can change, and what is covered depends on your particular policy rather than on the provider agreement. Confirm with Bupa before your appointment, and bring your card. Bupa Platinum Dental Provider.
For fees and instalment options, see Price Guide and Payment Plans.
Common questions
What are my pocket depths, and how many sites bleed?
Ask for both, and ask for them written down rather than summarised. “Your gums look a bit inflamed” cannot be compared with anything; “14 per cent of sites bled, deepest pocket 5 mm upper left” can.
Of the two, the bleeding score is the one that moves. It responds within weeks to a change in how you clean, which makes it the honest measure of whether your home routine is working. Pocket depth changes slowly and reflects attachment that has already been lost.
One piece of candour about the millimetre figures given further up this page: they are the thresholds in everyday clinical use, but we have not been able to attribute a specific numerical cut-off to an independent published guideline in our own reference set, so treat them as a working convention rather than a law. Ask your clinician which threshold they use, why, and — more usefully — what your own numbers were last time.
Why any of this is worth the trouble: a peer-reviewed review of periodontitis and general health describes severe periodontitis as affecting 10–15% of adults and moderate periodontitis 40–60% of adults, and calls the disease “highly prevalent, but largely hidden”. Hidden is the operative word. Diabetes Australia puts it plainly — gum problems “are often painless, however, in cases of advanced disease or sudden flare-up, pain can occur. At this stage, it may be too late for treatment to save the tooth.” Measurements exist because symptoms arrive late. See Bleeding Gums.
Has that changed since last time?
The single most useful question on this page, and the one almost nobody asks.
A set of gum measurements taken once is a description. The same measurements taken twice are evidence. Ask for the previous chart alongside today’s and look at three things: whether the bleeding percentage has fallen, whether pocket depths are stable, and whether recession is creeping. If the bleeding score has not moved, something in the routine is not reaching the places that matter, and that is a technique conversation rather than a product one.
Two things distort the comparison and are worth naming out loud. Smoking is a major risk factor — the same review notes it “significantly increases risk for periodontitis and severity of the condition” — and it also suppresses the bleeding that would otherwise warn you, so a smoker’s low bleeding score is not reassurance. Diabetes Australia specifically advises telling your dentist “if you are a current or previous smoker”. And pregnancy raises gum reactivity to the same amount of plaque, so a rise during pregnancy is not necessarily a fall in your standards.
If the numbers have not improved, ask what the clinician wants to see by the next visit, and by when.
Am I having a clean, or gum treatment?
Ask before the appointment rather than in the chair, because the two differ in what is done, how long it takes, what it costs and what happens afterwards.
A scale and clean is preventive. Periodontal therapy treats established disease: it reaches well below the gum, is usually done under local anaesthetic, often one quadrant at a time, and is followed by a re-assessment some six to eight weeks later to measure whether the pockets actually responded. If no one has told you when your response will be re-measured, you have probably been booked for a clean.
This is not an unusual or awkward question. With moderate periodontitis affecting 40–60% of adults in the review cited above, the chance that a given patient needs the second appointment rather than the first is not small. The failure mode is specific and common: a routine clean repeated every six months while attachment is quietly lost.
On cost, the two are billed differently, so ask for the item numbers and fees for each. As an indication of what sustained gum care can run to, Diabetes Victoria puts treatment for gum disease at “anywhere from $1,000 or even up to $2,000 per year, especially if you don’t have private health insurance” — that figure is given for people living with diabetes, and should be read as their estimate for that group rather than a general price. See Price Guide and Specialist Periodontists.
What is my recall interval, and why that one?
Six months is a default, not a finding, and you are entitled to the reasoning behind whatever interval you have been given.
No independent source in our reference set sets a single universal interval for everyone, and the guidance that exists says exactly that. Diabetes Australia’s oral health advice is that you should “see a dentist regularly for a check-up of your teeth and gums” and that “the dentist will advise you how often to return for check-ups and treatment. This may be more often if you have any of the above complications”. In other words the interval is a judgement about you, and it should be explained as one.
Things that commonly shorten it: existing attachment loss, heavy calculus formation, smoking, a dry mouth, orthodontic appliances, implants, and diabetes. The diabetes association is not small — one study cited in the review above found people with diabetes had roughly 2.9 times the odds of periodontitis (OR 2.90; 95% CI 1.40 to 6.03) after controlling for age, ethnicity, education, sex and smoking, and a separate cohort found that people with diabetes and severe periodontitis had 3.2 times the risk (95% CI 1.1 to 9.3) of combined cardiorenal mortality compared with the reference group.
One thing worth knowing if you live with diabetes: Diabetes Victoria points out that dental visits are not formally included in the Annual Cycle of Care for diabetes in Australia — blood pressure, HbA1c, cholesterol, kidney function, podiatry and eye checks are, and oral health is not. Nobody else’s checklist will prompt this one, so ask for your interval to be set deliberately and written down.
Where am I missing when I brush?
Ask to be shown, on your own teeth, at the appointment — not told in general terms. A plaque score exists for exactly this, and the pattern it reveals is usually consistent and fixable: the inside surfaces of the lower front teeth, the outer surfaces of the upper molars, and the gum line on whichever side matches your dominant hand.
The technique points that change the most are the two above — bristles angled towards the gum line at about forty-five degrees, and an electric brush guided slowly tooth by tooth rather than scrubbed. Diabetes Australia’s own list for protecting gums is short and worth having in front of you: brush twice a day with a soft brush and a pea-sized amount of fluoride toothpaste, clean between the teeth daily with floss or interdental brushes, eat a diet low in sugar, drink fluoridated tap water where available, and chew sugar-free gum to stimulate saliva flow. On the water: it reports that fluoridation “has been shown to reduce tooth decay by 26% to 44% in children and adolescents, and by 27% in adults” — which is a caries figure, not a gum one, and belongs in that column.
One substitution to avoid. Mouthwash does not do this job. The Australian position, quoted in Australian Prescriber, is that a rinse is “an adjunct to, not a substitute for, regular brushing and flossing” and “should never be the sole means of oral hygiene”; the ADA frames it the same way — alongside brushing, interdental cleaning and regular professional care, not as a replacement. If a rinse has quietly replaced flossing in your routine, that will show in the plaque score.
One timing note for anyone managing diabetes: after treating a low with fast-acting carbohydrate, Diabetes Australia advises drinking water to rinse the sugar and acid from the mouth once you feel well again, and waiting 60 minutes before brushing. Your diabetes team, not this page, is the place for the rest of that conversation.
Should I be using interdental brushes, and what size?
Probably yes where the space will take one, and the size is the whole question — a brush too small does nothing and one too large will not go in, so both fail silently.
The national guidance is clear that something has to clean between the teeth, without being prescriptive about which: Diabetes Australia advises to “clean between your teeth daily using floss or interdental brushes” and adds, usefully, “ask your dentist if interdental brushes can help you in caring for your teeth and gums” — which is exactly the question, and it implies the answer is individual. Sizing is not something to guess from a chemist shelf; ask your hygienist to try sizes at the appointment and write down which size goes where. Many mouths need two or three different sizes.
In fairness, one caveat about the claim earlier on this page that an interdental brush removes more plaque than floss where the space allows: that is a widely held clinical position, but we cannot attribute it to an independent published source in our own reference set, so it is stated here as the practice’s view rather than as settled evidence. What is not in doubt is that the space between teeth has to be cleaned daily by something, and that the something has to fit.
If your gums bleed when you first start using them, that is usually inflammation rather than damage, and it generally settles within a week or two of consistent use. If it does not, have it looked at rather than stopping.
My gums bleed when I brush. Should I stop cleaning them until the appointment?
Continue gentle cleaning and arrange a dental assessment; bleeding is a reason to have the gums checked, not to leave plaque undisturbed. Healthdirect's gum-disease guidance recommends gentle brushing twice daily even when gums bleed, alongside cleaning between teeth and professional care. Tell the clinician when the bleeding began and about swelling, loose teeth or other changes. They can identify the cause and show you a suitable technique.
Does a hygiene appointment include a full dental check-up?
Confirm the scope when booking. A hygiene visit includes assessment relevant to the care being provided, but you should not assume that every examination, x-ray or assessment of a separate concern is included in that appointment or fee. Describe pain, a broken tooth or another specific problem in advance so the practice can arrange the appropriate clinician and time. Ask whether a separate dentist appointment is recommended.
If my teeth feel clean afterwards, why would I need further gum treatment?
Smooth tooth surfaces do not show whether disease below the gumline has been controlled. Gingivitis and periodontitis require different assessment and follow-up; Healthdirect explains that periodontitis can be controlled but needs ongoing care. Ask the clinician to explain your diagnosis, the findings behind it, the treatment already completed and how the response will be checked. A clean feeling is welcome, but it is not a substitute for reassessment.
Can I ask for the clean to be paused or divided into appointments?
Yes, tell the clinician if you need a pause, feel discomfort or are finding the appointment difficult. Discuss this beforehand if previous experiences have made you anxious. Ask what comfort measures or appointment arrangements would suit the proposed care and whether staging it would change the fee or number of visits. Agreeing on a stop signal can make it easier to communicate during treatment. The clinician should explain the plan before proceeding.
Related pages: General Dentistry, Bleeding Gums, Bad Breath, Tooth Fillings, Teeth Whitening, Specialist Periodontists, Children's Dentistry, Dental Implants.
Practical details
| Address | Level 1, 220 Collins Street, Manchester Unity Building, Melbourne VIC 3000 |
| Phone | 13 13 96 |
| theteam@smilesolutions.com.au | |
| Monday – Friday | 8.00am – 6.00pm |
| Saturday | 8.30am – 1.30pm |
| Sunday | By appointment |
| Usual frequency | Every six months, or as advised |
| Higher-risk interval | Every three to four months |
| Healthy pocket depth | 1–3 mm |
| Performed by | Oral Health Therapists / dental hygienists |
| Technology | Airflow, ultrasonic scaling |
| Hygiene department since | 1993 |
| Parking | Wilsons Parking, Flinders Lane (between Swanston and Russell) |
Registration of hygienists, oral health therapists and specialist periodontists can be verified free on the AHPRA public register at ahpra.gov.au.
General information only — it is not a diagnosis, a treatment plan, a quote or a promise of any particular clinical outcome, and it does not replace advice from your treating practitioner. The right cleaning interval, the technique used and how your gums respond vary between individuals, and a professional clean prevents disease rather than guaranteeing its absence. Fees and health fund rebates are indicative and subject to change; confirm at your consultation and with your fund.
Smile Solutions trades under ABN 28 193 514 103.
Images on This Page
-
https://www.facebook.com/tr?id=800557773428361&ev=PageView&noscript=1
(no alt text)
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/10/calendar_month.svg
(no alt text)
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/images/smile_solutions_logo_white.png
Smile Solutions Logo
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/images/smile_solutions_logo_purple.png
Smile Solutions Logo
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/11/Smile-Solutions-4.png
Smile Solutions - Melbourne CBD
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/11/Dental-Payment-Plans.png
Dental Payment Plans
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/09/Smile-Solutions-Level-10.png
Smile Solutions Level 10
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/09/Airflow.jpg
Airflow at Smile Solutions
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/09/c20ad0172e16ad37cb5b692f6ef93b9ca2f833a1.jpg
Dedicated team of Oral Health Therapists
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/09/AE.jpg
Specialist periodontal care
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/08/69a44c30c93ce196d539cc5520080df52a5f3f88-scaled.jpg
69a44c30c93ce196d539cc5520080df52a5f3f88 scaled
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/images/family_owned_bussiness.png
Family Owned Business
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/icons/icon--phone.svg
Smile Solutions Contact
-
https://www.facebook.com/tr? id=800557773428361&ev=PageView&noscript=1
(no alt text)