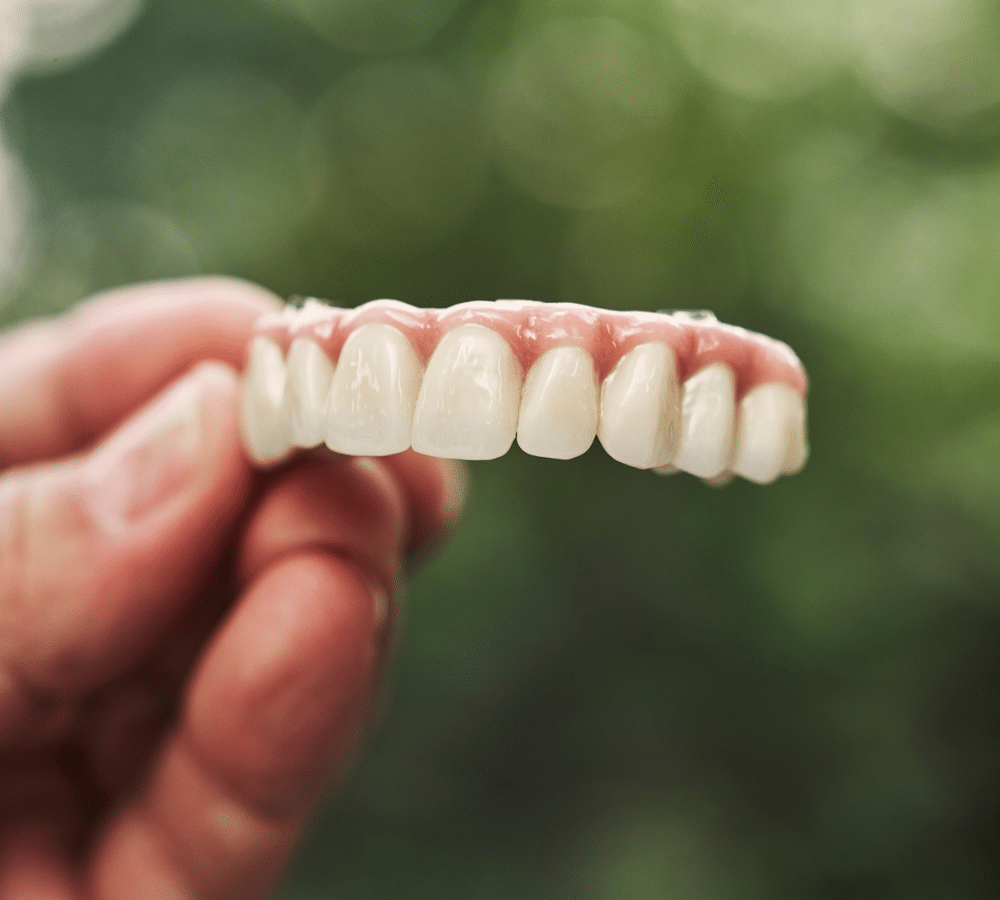
Who should I see for dental implants?
It depends on the case, and on which of the two stages you are asking about:
- The surgical stage — placing the titanium fixture into the jawbone beneath the gum
- The restorative stage — fitting the crown onto that fixture
There is no dental specialty devoted exclusively to implants. General dentists, particularly experienced ones, can attend to both stages. But the more complicated the case — multiple missing teeth, depleted bone, cosmetic challenges, or bite complications — the stronger the case for consulting a specialist, or at least seeking a specialist second opinion. See Specialist Care, Complex Dentistry and Second Opinions & Corrective Dentistry.
The relevant specialists
| Stage | Appropriately qualified specialists |
|---|---|
| Surgical | Oral and maxillofacial surgeons, oral surgeons, and periodontists |
| Restorative (the crown) | Prosthodontists |
All of these are Dental Board registered specialists — that is, they hold formal specialist registration following recognised postgraduate training. See Dentists & Registered Specialists.
What "specialist" means, precisely
The word has a legal meaning in Australian dentistry, and knowing it is what makes the rest of this page usable.
The Dental Board of Australia states that “There are 13 dental specialties in Australia which are approved by the Australian Health Workforce Ministerial Council”. They are: dento-maxillofacial radiology, endodontics, forensic odontology, oral and maxillofacial surgery, oral medicine, oral and maxillofacial pathology, oral surgery, orthodontics, paediatric dentistry, periodontics, prosthodontics, public health dentistry (community dentistry), and special needs dentistry.
Implant dentistry is not among them — which is the whole basis of the warning below.
To hold specialist registration, the Board requires an applicant to hold a qualification in the specialty, to meet all the requirements for general registration as a dentist, and to have “completed a minimum of two years general dental practice”. That last requirement is easy to overlook and worth knowing: a registered specialist has been a general dentist first.
The Board also confirms where to check. AHPRA “publishes an online register of all dental practitioners” which “includes details of the specialty or specialties for dentists who hold specialist registration”.
A warning about titles
This is the most practically useful thing on the page.
Be cautious of titles such as “implant surgeon”, “implantologist” or “implant dentist”. These are not recognised specialties in Australia, and clinicians using them do not necessarily hold any qualification beyond that of a general dentist.
That is not an argument against general dentists placing implants — many do so well, and experience matters. It is an argument for knowing what you are looking at. A self-adopted title tells you what a clinician is interested in, not what they are registered as.
Australian advertising law is explicit about this. AHPRA's guidelines for advertising a regulated health service state that “Only a registered health practitioner who holds specialist registration in a recognised specialty or an endorsement may use the relevant specialist title” in advertising, and that this “includes in the name of the business or other advertising to the public”. Misuse of a protected title is an offence under the National Law, and penalties can apply.
The guidelines go further, to language that stops short of a protected title but still misleads. Where a practitioner does not hold specialist registration, the National Boards consider that advertising using “the words, or variations of the words or phrases ‘specialist’, ‘specialises in’, ‘specialty’, or ‘specialised’” is likely to mislead the public into believing they hold specialist registration. The guidelines name the wording that is acceptable instead: “Words such as ‘substantial experience in’ or ‘working primarily in’ are less likely to be misleading.”
So the phrasing on a practice website is itself informative. “Substantial experience in implant dentistry” is a careful, lawful description by a general dentist. “Implant specialist” from someone without specialist registration is not.
One nuance on the word surgeon, because “implant surgeon” invites it. The National Law was amended to restrict the title surgeon among medical practitioners to those holding specialist registration in surgery, obstetrics and gynaecology, or ophthalmology. AHPRA notes that this change “does not change the rules for use of protected titles by health practitioners with specialist registration in the dental and podiatry professions, or for dentists using the title dental surgeon.” In other words, that particular reform does not settle what a dentist may call themselves — so check the register rather than reading the title.
How to check, in two minutes: search the practitioner's first name and family name on the Australian Health Practitioner Regulation Agency (AHPRA) register. A profile listing “Dental Practitioner — General” is a general dentist. One listing “General & Specialist” holds specialist registration, and names the specialty. The Smile Solutions clinicians and their registrations are listed on Our Team.
Referrals and records
You often do not need a referral to see these specialists for implants — you can make an appointment directly. See Contact Us.
Your scans, radiographs and records can be transferred from your existing dentist, so there is no unnecessary duplication of imaging or of cost. Ask for them to be sent before your appointment.
Cost
Implant costs reflect the two stages, and quotes vary considerably. The itemised breakdown is on Dental implant costs in Melbourne; see also How much do dental implants cost?, the Price Guide and Payment Plans. A few things worth understanding when comparing quotes:
- Check the registration level of the practitioners quoting. Specialists generally charge more than general dentists, particularly on more involved cases — so a like-for-like comparison requires knowing who is doing the work.
- Compare the whole treatment, not the fixture. A quote may or may not include the surgical placement, the abutment, the crown, imaging, any bone grafting, and follow-up.
- Ask what happens if something fails, and who bears the cost.
- Ask which implant system is used, by name, and have it recorded in your file. In fifteen years, a documented, widely supported system is far easier to service. See What are the different types of dental implants?.
Payment plan options are available. Where a plan is advertised as interest free, that describes the plan term only — a deposit may be required, an establishment fee and ongoing account fees may apply, and charges can apply if the balance is not cleared within the agreed period. The applicable terms depend on the provider and the amount financed, and are set out in writing before you commit — ask what the deposit and the establishment fee are, in dollars, and what the total will be by the end. Payment Plans.
On Medicare: a rebate may be available in certain circumstances where treatment is provided by an oral and maxillofacial surgeon, who is also a registered medical practitioner. This is not automatic and depends on the nature of the procedure and your individual circumstances — check with the practice and with Medicare before assuming it applies. Private health insurance is a separate question again, and dental cover typically has annual limits and waiting periods.
What else to ask
- What are the alternatives — a bridge, a denture, or leaving the space — and why is an implant preferred here? See Bridges, implants or dentures and Implant versus bridge for a single tooth replacement
- Is bone grafting likely? That adds time, cost and a second surgical site
- Who places it, and who restores it? If two clinicians are involved, how do they coordinate? A single multidisciplinary practice removes the handover problem — see Dental Implants at Smile Solutions
- What is the maintenance schedule and its ongoing cost? Implants need lifelong professional monitoring and cleaning — Dental Cleans & Hygienists
- Could the tooth be saved instead? If extraction is being proposed for a tooth you were not expecting to lose, ask about root canal treatment and see an endodontist before agreeing
The risks, briefly
Implants are a well-established treatment, and they are not risk-free:
- Failure to integrate, early or years later. Smoking, poorly controlled diabetes, poor oral hygiene and heavy grinding all raise the risk substantially. See Diabetes and oral health and TMD and Teeth Grinding
- Peri-implantitis — inflammatory bone loss around the implant, harder to treat than gum disease around a natural tooth. See What is periodontal disease?
- Surgical risks — bleeding, infection, sinus complications in the upper jaw, nerve injury with altered sensation in the lower lip and chin
- The crown is not permanent even where the implant is
Smoking is worth singling out, because it is the largest modifiable risk factor for implant failure and many surgeons will raise stopping before proceeding.
What the failure rate actually looks like
It helps to have a number rather than an adjective. A retrospective analysis of one Israeli health fund's electronic dental records, covering 158,824 implants placed in 53,874 patients between 1 January 2014 and 31 December 2022, reported an overall implant survival rate of 97.79%, with a total failure rate of 2.21%. Early failure — during osseointegration, before the crown goes on — accounted for 1.56%, and failures within the first year for 1.59%.
Three findings from that dataset are worth carrying into a consultation:
- The first year is when it happens. Failure incidence was highest in the first year after placement and dropped substantially afterwards. That is the period in which to report any looseness, discomfort or swelling promptly rather than waiting for a review.
- Site matters. Failure rates in the maxillary molar region (3%) and the central incisor region (3.37%) were approximately double those seen at other implant sites. Ask where yours is going and whether that changes the plan.
- More implants is not riskier. The failure rate for multiple implants was only 0.18% higher than for single implants — a difference the authors report as not statistically significant.
On risk factors, the same paper cites a meta-analysis concluding that significant risk factors for early failure included smoking habits, implants shorter than 10 mm, and implants placed in the maxillary region.
Two honest caveats. This is a single retrospective study drawn from one clinical database, and its own authors flag both limitations and call for larger, more diverse populations. And a survival rate is not a success rate — an implant can survive while causing trouble. Treat the figure as a reasonable order of magnitude, not a promise about your case.
Common questions
I have osteoporosis. Does that rule an implant out?
Probably not, but it changes the planning conversation. A systematic review indexed on PubMed appraised the evidence on osteoporosis, osseointegration and implant survival across 24 studies covering 2,102 patients and 5,954 implants, with follow-up ranging from one month to 25 years and four studies running beyond ten years. Its findings: “All studies' survival rate was higher than 90%, even for osteoporotic patients”; most studies found no difference between osteoporotic and healthy patients in marginal bone loss or bone-to-implant contact; and “Osteoporosis status was not a risk factor for dental implant failure”. The picture is not uniform — the same review notes that some studies reported lower stability scores for implants placed in osteoporotic sites and a higher risk of failure. Its conclusion is the sentence worth taking to a consultation: “Osteoporosis is not a contraindication for dental implant placement. Osseointegration in patients with osteoporosis is feasible; however, planning must be cautious and personalized for the placement of dental implants.”
What that review looked at was the diagnosis, not the treatment for it. So tell the surgeon about every bone medicine you take or have taken — tablets, and particularly anything given by injection or infusion at a clinic or hospital — with approximate dates, because the relevant history can reach back years. Bring the packaging or a current medicines list rather than relying on memory, and do not stop or alter anything without the prescriber's advice.
Once it is in, how much upkeep is it, and how often does something go wrong?
Often enough to plan for, which is the part quoted survival rates hide. An ITI consensus statement on implant survival and complications reports that for implant-supported fixed bridgework, “peri-implantitis and soft tissue complications occurred in 11.7% of implants after 5 years”, and then states the overall position plainly: survival rates are high, “However, biologic and technical complications occurred in about half the cases after 5 years of function.”
A complication is not a failure. A loosened screw, a chipped ceramic surface or inflamed tissue all count, and the implant can be still in place and still counted as a survivor. But each one is an appointment, and some are a cost. So budget for a professional clean and check at whatever interval your clinician sets, expect periodic radiographs rather than none, and treat bleeding or tenderness around an implant as a reason to be seen rather than watched. Bone lost around an implant does not simply return: the same ITI statement, reviewing surgical treatment of peri-implantitis, records that “the amount of bone regeneration and re-osseointegration varied substantially”. That is an argument for early review, not for alarm.
Can an implant be joined to one of my own teeth in the same bridge?
It can be, and the ITI consensus statement above is the reason to ask why before agreeing. Comparing the two designs over the same follow-up periods, for the implants themselves:
| Bridge design | Implant survival at 5 years | at 10 years |
|---|---|---|
| Supported by implants only | 95.4% | 92.8% |
| Supported by an implant and a natural tooth | 90.1% | 82.1% |
The bridgework follows the same pattern — 95.0% at five years and 86.7% at ten where implants alone carry it, against 94.1% and 77.8% where an implant and a tooth share the load.
Read those as what they are: cumulative survival rates pooled from cohort studies, with thin evidence at the ten-year mark in particular (the ten-year implant-and-tooth bridge figure rests on three studies and sixty bridges). Connecting an implant to a natural tooth is sometimes still the right plan for a particular mouth. But if it is being proposed, ask what the all-implant alternative would cost and why it was set aside.
My gums bleed when I brush. Should that be sorted out before an implant goes in?
Yes, and the reason is worth understanding rather than being told to floss more. Bleeding is the visible end of a process described in Periodontitis and diabetes: a two-way relationship, a review on PubMed Central: inflammation extends past the gum, the collagen fibres of the periodontal ligament break down, a pocket forms between gum and tooth, and “the resorption of the alveolar bone ... occurs in parallel with the progressing attachment loss”. The same paper is blunt that “the tissue destruction that occurs is largely irreversible”, and that in the early stages the condition “is typically asymptomatic; it is not usually painful, and many patients are unaware until the condition has progressed enough to result in tooth mobility”.
Two practical consequences. First, it cannot be assessed by looking: “‘Pocketing’ is not evident on simple visual inspection, and assessment using a periodontal probe is essential” — so ask whether your gums have actually been probed and charted, not just looked at. Second, an implant is placed into the same bone that active disease is removing, and the inflammatory condition around an implant is harder to manage than around a natural tooth. Sequencing the gum treatment first is standard, not a delaying tactic. See What is periodontal disease? and periodontists.
Who do I raise a concern with if something goes wrong, or if a clinic's advertising looks wrong?
Those are two different channels, and knowing which is which saves months.
Concerns about a practitioner's health, conduct or performance go to the regulator. AHPRA's advertising guidelines describe the National Boards as responsible for registering practitioners, setting the standards they must meet, and “managing complaints and concerns (notifications) about the health, conduct or performance of practitioners”. Two states route these elsewhere: in New South Wales they are managed by the Health Care Complaints Commission and the Health Professional Councils Authority, and in Queensland jointly by the Office of the Health Ombudsman and the National Boards and AHPRA.
Concerns about advertising — a protected title used by someone without specialist registration, for example — are a separate stream, handled under the National Scheme's advertising compliance and enforcement strategy. The guidelines say a complaint can be made using the complaint form on the AHPRA website, and that you can “call Ahpra on 1300 419 495 for further information on making a complaint about advertising”.
Neither channel is the first move for a clinical problem you simply want put right. Raise that with the practice, in writing, and ask for your records and radiographs at the same time — they are the evidence for anything that follows.
Does this article replace an individual dental assessment?
No. It provides general information. Symptoms, suitability, risks and treatment choices depend on examination and, where indicated, imaging or other records from an appropriately registered practitioner.
Related reading
- What do I need to know about dental implants?
- Things to consider when choosing All-on-4
- Mini implants versus standard dental implants
- Dental tourism: the risks involved
- Why would I need to see a dental specialist?
Practical details
Oral and maxillofacial surgery, periodontics and prosthodontics are recognised dental specialties. Specialist registration can be verified on the AHPRA register, or by calling 1300 419 495.
Smile Solutions, Level 1, 220 Collins Street, Manchester Unity Building, Melbourne VIC 3000 — getting here. Phone 13 13 96, or theteam@smilesolutions.com.au. Monday–Friday 8.00am–6.00pm, Saturday 8.30am–1.30pm, Sunday by appointment.
Published 3 April 2018, by Dr Kia Pajouhesh. General information only; it does not replace advice from your treating practitioner. Outcomes vary between individuals; all surgical and implant treatment carries risks. Statements attributed to the Dental Board of Australia and AHPRA are those bodies' own; the survival and complication figures are from the published studies described and are not this practice's own results. Rebate and insurance information is general and subject to change. Payment plan terms are set by the credit provider and change; confirm current terms directly before you commit.
Smile Solutions trades under ABN 28 193 514 103.
Images on This Page
-
https://www.facebook.com/tr?id=800557773428361&ev=PageView&noscript=1
(no alt text)
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/10/calendar_month.svg
(no alt text)
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/images/smile_solutions_logo_white.png
Smile Solutions Logo
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/images/smile_solutions_logo_purple.png
Smile Solutions Logo
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/11/Kia-150x150.jpg
Dr Kia Pajouhesh
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/11/All-on-4-Dental-Implants-Smile-Solutions.png
All-on-4 Dental Implants Smile Solutions
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/09/Wisdom-Teeth-Smile-Solutions-300x300.png
Smile Solutions Dentist Melbourne
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/11/TMD-Teeth-Grinding-Smile-Solutions-300x270.png
Woman holding her face, looking concerned.
-
https://www.smilesolutions.com.au/wp-content/uploads/2026/07/Photography-and-Facial-Analysis-300x270.jpg
Photography and Facial Analysis
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/images/family_owned_bussiness.png
Family Owned Business
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/icons/icon--phone.svg
Smile Solutions Contact
-
https://www.facebook.com/tr? id=800557773428361&ev=PageView&noscript=1
(no alt text)
-
https://bat.bing.com/action/0?ti=25148060&tm=gtm002&Ver=2&mid=21b44d61-c074-4d00-98b1-6d7386919739&bo=1&sid=1afdfe60ab2711f18be5a9f7d3ae0522&vid=1afe87a0ab2711f184704bea1d09af1d&vids=1&msclkid=N&pi=918639831&lg=en-US&sw=800&sh=600&sc=24&nwd=1&tl=Who%20should%20I%20see%20for%20dental%20and%20teeth%20implants,%20and%20are%20these%20costly%3F%20-%20Smile%20Solutions&p=https%3A%2F%2Fwww.smilesolutions.com.au%2Fdental-articles%2Farticle%2Fwho-should-i-see-for-dental-and-teeth-implants%2F&r=&evt=pageLoad&sv=2&cdb=AQAQ&rn=448951
(no alt text)