How long do dental fillings last?
Everything in dentistry has a finite lifespan
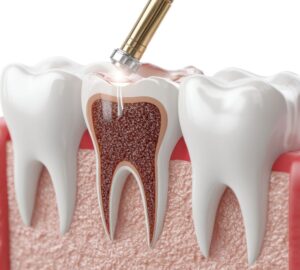
When a tooth is damaged by decay or trauma, fillings replace the lost structure.
Dentists work to maximise the lifespan of every filling by using the best materials under ideal working conditions. But everything in dentistry has a finite lifespan, and fillings are no different.
The answer to how long one will last is complex, because each cavity and each filling is unique and several factors interact. Those factors fall into three groups: the material, the placement, and you.
The material
Fillings today are made from one of two main types of material: porcelain, and a soft plastic. They have different lifespans because their properties differ. Porcelain, amalgam or composite resin? describes each material in full.
Porcelain (CEREC) fillings
Customised restorations shaped according to a 3D scan of the tooth cavity, then milled chair-side from a high-strength, aesthetically appealing porcelain block — see same-day CEREC restorations and how the CEREC process works.
Porcelain is generally the preferred filling material for medium or large cavities, and porcelain fillings are considered the definitive fix for the tooth.
Research has shown success rates of at least 95 per cent after 10 years — the study is cited at the foot of this page. Read it as one study of one system rather than as a settled figure: chairside ceramic survival is reported across a scatter of practice-based series with differing definitions of failure, and it is not the kind of claim a systematic review has pinned down. Ask what the evidence is for the particular material and design proposed for your tooth.
Composite (plastic) fillings
A soft plastic material adapted to the cavity and set hard with a blue light.
These are generally weaker and not dimensionally stable over time. As a result they have a relatively short lifespan — generally three to five years, depending on the size of the filling. The same material used cosmetically on front teeth, where the load is lower, lasts longer — see will composite bonding look natural, and how long will it last? and the composite bonding service page.
The comparison
| Composite | CEREC porcelain | |
|---|---|---|
| Typical lifespan | 3–5 years | At least 95% success at 10 years |
| Best suited to | Smaller cavities | Medium or large cavities |
| Made | Directly in the mouth, one appointment | Milled chair-side from a 3D scan |
Porcelain fillings and composite fillings: the differences and costs adds fees to this table; published fees are in the price guide.
The words not dimensionally stable over time are doing important work. Composite shrinks slightly as it sets and continues to change over years — and a filling that changes shape opens a gap at its margin. That gap is where the next problem starts, and it is usually found on x-ray rather than by symptoms.
The size of the cavity is the deciding factor, not preference. A small composite filling in a small cavity may serve well. The same material stretched across a large cavity is being asked to do something it is not strong enough or stable enough to do. Past a certain size the honest answer is neither — the tooth needs a crown; what types of dental crown are available? covers that step.
Where the independent evidence supports the size rule, and how far
The most directly relevant independent evidence is not about fillings in sound teeth but about teeth that have cracked — which is where large fillings tend to end up. The European Society of Endodontology's 2024 position statement on longitudinal cracks and fractures of teeth reports that cracked teeth “managed with direct bonded composite restorations may be more likely to require root canal treatment and/or further repair of fractured restorations compared with CT managed with cuspal coverage restorations”, across three cited studies. Cuspal coverage is what an onlay or a crown does and a filling does not.
Two honest limits on that. The same statement says plainly that “there is no clear evidence on the most suitable restorative treatment approach” for a cracked tooth, so the direction is supported and the ranking is not. And it puts a number on where these teeth can end up regardless of material: the reported need for root canal treatment after restorative management of a cracked tooth runs at between 7.7% and 20%.
The same statement also lists what predisposes a tooth to crack in the first place, and two items on its list belong on this page: “compromised structural integrity” and, among contributory factors, “stress generated from restorative procedures” and “thermal expansion, contraction, and/or corrosion of restorative materials”. That is the independent version of the argument about large old fillings — not that the filling was bad, but that a heavily restored tooth has less of itself left to resist load, and that the materials inside it move with temperature.
One honest qualification to the comparison table. In a narrower population — teeth that have already had root canal treatment — a systematic review and meta-analysis comparing the clinical performance of direct composite resin against indirect restorations found no differences in tooth survival (Long-term tooth survival and success following primary root canal treatment, PMC). That is not the same population as a routine filling in an otherwise sound tooth, and it does not overturn the size rule above. It is a useful reminder that the choice of material is rarely the only thing deciding the outcome — which is the subject of the next two sections.
The placement
How a filling is placed has a big impact on how long it lasts.
There is a saying in dentistry: the seal is the deal.
A filling is only as good as the quality of the bond between the tooth and the filling material. Anything that strengthens that bond increases the lifespan.
Why rubber dam matters
All materials that rely on bonding to tooth structure — both CEREC and plastic fillings — are sensitive to moisture, and will not stick well if there is humidity, water or saliva in the area.
So fillings should ideally be placed under rubber dam protection — a thin rubber sheet that protects the filling from contamination by moisture, much like a raincoat for the tooth.
Rubber dam is mandatory for root canal treatment, and given how well it works, it should be the standard of practice for routine fillings as well. Root canal treatment: who and what is involved? describes its role there.
This is worth knowing as a patient, because it is not universal practice. A filling placed in a wet field can fail years earlier than the same material placed in a dry one — and you cannot tell by looking at the finished result. It is a reasonable thing to ask about, in the same spirit as understanding your treatment or seeking a second opinion.
What the published evidence actually shows
Isolation has been studied directly, though mostly in root canal work rather than in routine fillings — so the figures below describe root-treated teeth, and are quoted here because the underlying material science does not change between the two procedures.
In large registry studies from Taiwan and Korea, it was concluded that registration of usage of a rubber dam significantly positively affected the 5-year tooth survival rate (Tooth survival after endodontic treatment, International Endodontic Journal, 2023, citing Kwak et al. 2019 and Lin et al. 2014). The same review observes that where adequate isolation and restoration are harder to achieve, that difficulty “may adversely affect the seal against microbial leakage and the longevity of the restoration”.
The British Dental Journal states the requirement for root canal treatment plainly: the use of dental dam is “mandatory from a patient safety, as well as infection control standpoint”. There is no equivalent published mandate for ordinary fillings. That is the honest position — the case for using it routinely is an argument from the same physics, not a rule.
Two further findings from that literature are worth carrying across.
The seal matters as much as the work underneath it. A systematic review comparing the impact of the coronal restoration against the quality of the root canal treatment itself “concluded that coronal seal was as important as the quality of the endodontic treatment in terms of treatment success” (Success and failure of endodontic treatment, British Dental Journal). For a filling, the equivalent claim is the one this practice has always made: the margin is not a finishing detail, it is the treatment.
A temporary filling is not a resting state. The same source records evidence of an increased failure rate of endodontic treatment with temporary restorations, and advises that the definitive restoration should be provided as soon as possible. If you are carrying a temporary, the appointment to replace it is not optional housekeeping — what do I do if a temporary filling comes out? covers the immediate problem, and specialist endodontists the work underneath it.
What you control
Every filling in the mouth is under stress:
- Daily eating and drinking
- Temperature changes from hot and cold foods and drinks
- Parafunctional habits such as grinding or clenching
That third one is the biggest patient-side variable. Grinding loads a filling far beyond what chewing does, and it does so for hours at a time, unconsciously, at night. If you grind, the honest expectation for any restoration is shorter — and an occlusal splint is not an optional accessory. The European Society of Endodontology's 2024 statement lists “parafunction and/or unfavourable occlusal arrangement” among the predisposing factors for every category of tooth crack it describes, which is independent support for taking it seriously. TMD and teeth grinding is the service page; night-time tooth grinding and clenching and how can I stop grinding my teeth when I sleep? cover what can be done about it.
That is not only clinical intuition. In a long-term study of root-treated teeth, the use of a night guard was identified in the statistical model as a protective factor for survival of the tooth (Long-term tooth survival and success following primary root canal treatment, PMC). Again the population is narrower than a routine filling — but a splint is one of the few things on this page that is entirely within a patient’s control. Be aware of the limit of that claim: we could find no study measuring whether a splint extends the life of a filling specifically, and the wider splint literature is about jaw symptoms rather than restorations, where Cochrane's 2024 review rated the evidence very low certainty throughout.
If the filling was needed because of decay
The priority is minimising the risk of new decay in future, which is what causes early replacement of an otherwise sound filling.
That may involve changing certain habits and adding protective factors to your home-care routine — preventing dental decay, the benefits of fluoride, the ideal daily routine for oral hygiene, and regular hygiene appointments. The Australian Dental Association's own list of the essentials is short and worth measuring your routine against: brushing for two minutes twice a day, an age-appropriate fluoride toothpaste, cleaning between the teeth once a day with floss or interdental brushes, and regular professional check-ups and cleaning.
The point beneath this: a filling treats the damage, not the cause. If the conditions that produced the first cavity are unchanged, decay will appear again — commonly at the margin of the new filling, where it is hardest to detect. Your decay risk profile and the best ways to prolong the life of your filling should be discussed at your appointment. How does your diet affect your teeth? and how does sugar affect your dental health? cover the largest of those conditions.
Common questions
What actually happens if I leave it?
The sequence is slow, and the part that catches people out is that it includes a stretch where the pain stops.
The Australian Journal of General Practice sets out the progression: “the onset of a dental abscess is usually slow over many months. Dental decay takes several months to reach the dental pulp. Pulpitis results in pain that is poorly localised. When pulp necrosis finally occurs, there is no pain. However, when an acute periapical abscess develops, a severe well-localised pain develops.”
Read that sequence again for the middle step. The toothache stopping does not mean the tooth got better. It can mean the nerve has died, and the next event is an abscess. The same paper notes that by the time an abscess arrives, “all patients have had intermittent episodes of pain as a warning that something is wrong.”
The other thing it says is worth holding onto, because it is the argument for not panicking either: at the abscess stage, “the dental abscess is easily treated by extraction or root filling.” What changes the picture is an infection that starts to spread — swelling moving toward the eye or down into the neck, difficulty swallowing or breathing, fever with increasing swelling. That is a hospital emergency rather than a dental appointment.
Two things from the wider Australian literature are worth adding, because they answer the two ways people usually try to avoid the appointment. The first is scale: the Australian Institute of Health and Welfare records about 88,600 potentially preventable hospital admissions for dental conditions in Australia in 2023–24 — its own definition of the term being “hospital stays for dental conditions considered avoidable with timely non-hospital care”. That figure covers all dental causes rather than infection alone, and the AIHW publishes no usable breakdown by cause or age group on the page it appears on. The second is the shortcut that does not work. The Royal Australian College of General Practitioners puts it in six words: “Antibiotic treatment without dental treatment to remove the cause always fails.” A course of antibiotics can buy time on a spreading infection; it does not treat the tooth.
So the honest answer to leaving a small cavity is not that something terrible happens next week. It is that the cheapest, smallest and most predictable version of the treatment is the one available now, and every stage after this one costs more tooth. The stages of dental decay sets the sequence out in full.
My old filling looks fine and doesn't hurt. Why does it need replacing?
Because neither of those two things is how a failing filling announces itself.
As set out above, the usual failure point is the margin — the join between filling and tooth — and decay starting there is typically found on a radiograph rather than seen or felt. The comfort half is answered by the progression quoted in the previous question: absence of pain is compatible with a live problem, and in one specific case is actually a sign of one.
The European Society of Endodontology makes the same point about cracks, with a figure attached, and it is a useful corrective in both directions. A large practice-based study of 2,858 teeth seen by 209 dentists found 45% of cracked teeth were symptomatic — meaning most were not — while the statement also records that only 2% of cracked teeth with a living pulp showed any evidence of the crack on a radiograph, and that cone-beam CT “is not predictable in detecting cracks”. Symptoms are a poor guide, and so is an x-ray taken on its own. That is why the examination matters and why a finding is sometimes watched rather than treated.
That said, “it needs replacing” is a clinical judgement, and it is entirely reasonable to interrogate it. Four questions that will get you a useful answer:
- Can I see it? Ask to be shown the radiograph or the intraoral photograph, and ask what specifically is being pointed at.
- What has changed since last time? A margin that has been noted and watched for two years is a different situation from one seen today for the first time.
- Is this active or is it being monitored? Not every finding needs treating this month, and a competent answer will distinguish the two.
- What happens if we review it in six months instead? The answer to that is part of informed consent, and it should be specific.
If the answers do not satisfy you, a second opinion is a normal step rather than a discourtesy.
Is porcelain worth the extra?
Sometimes, and the arithmetic is easier than the sales conversation.
Use the two figures from the table above. A composite filling has a typical lifespan of three to five years; the CEREC study cited at the foot of this page reports success rates of at least 95 per cent after ten years. Over a decade, then, the composite option is not one fee — it is potentially two or three, plus the appointments. Whether it still comes out cheaper depends on the actual fees, which are in the price guide and worth asking about as a total rather than per item.
But cost is the second question. The first is the size of the cavity, and that decides more than preference does: composite is well suited to small cavities and is being asked to do something it is not dimensionally stable enough to do when it is stretched across a large one. Past a certain size, neither is right and the tooth needs a crown.
Three cautions before treating the ten-year figure as a promise. It describes a study population rather than your tooth. The placement and grinding factors set out above can move it a long way in either direction. And the figure comes from a single named study of one chairside system — it is not a pooled estimate from a systematic review, and it has a definition of “success” you would need the paper to read. The Australian Dental Association's general caution about restorations applies whichever you choose: having a crown, bridge or veneer “does not mean no treatment will ever be required again for the tooth or teeth”. No restoration is permanent; the realistic comparison is between longer and shorter, not between temporary and forever.
I've been carrying a temporary filling for months. Does that matter?
Yes, and it is worth bringing forward rather than waiting for it to fail.
A temporary is designed to seal the tooth for a defined interval — between appointments, or while a symptom settles — not to be a resting state. The endodontic literature quoted above is direct on the point: there is evidence of an increased failure rate of treatment where temporary restorations are left in place, and the recommendation is that the definitive restoration should be provided as soon as possible. The mechanism is the one this whole page turns on: a temporary material does not seal as well or for as long, and once the seal leaks, bacteria reach the part of the tooth the treatment was meant to protect.
Two practical points. If the temporary has come out, the tooth is unsealed now — what do I do if a temporary filling comes out? covers the immediate steps. And if the reason you have not returned is the cost of the definitive restoration, say so when you ring rather than staying away; what can be staged, and in what order, is a conversation worth having.
Related reading
- Why do I need a filling?
- Can you reverse tooth decay?
- The stages of dental decay
- What do I do if a temporary filling comes out?
- Why do I bite my cheek after a filling?
- Why does a cracked tooth hurt so much?
- What does restorative dentistry mean?
Reference
Posselt A, Kerschbaum T, “Longevity of 2328 chairside CEREC inlays and onlays”, International Journal of Computerized Dentistry, 6: 231–248.
Fransson H, “Tooth survival after endodontic treatment”, International Endodontic Journal, 2023.
“Success and failure of endodontic treatment: predictability, prognosis and retreatment”, British Dental Journal, 2025.
“Long-term tooth survival and success following primary root canal treatment”, PMC.
Bayetto K, Cheng A, Goss A, “Dental abscess: a potential cause of death and morbidity”, Australian Journal of General Practice 2020;49(9) — the progression of untreated caries to abscess quoted in Common questions.
Patel S, Bhuva B, Mannocci F and colleagues, “Position statement on longitudinal cracks and fractures of teeth”, European Society of Endodontology, International Endodontic Journal 2024;57(11):1552–1565 — the cracked-tooth findings on restorative approach, predisposing factors, radiographic detection and symptoms.
Australian Institute of Health and Welfare, Oral health and dental care in Australia (2026) — potentially preventable hospitalisations.
Royal Australian College of General Practitioners — the primary-treatment principle quoted on antibiotics.
Australian Dental Association — Policy Statement 2.3, community oral health promotion and oral hygiene, and its consumer guidance on crowns, bridges and veneers.
Cochrane Review CD012850, Occlusal interventions for managing temporomandibular disorders (2024).
Practical details
Written by Dr Maliha Siddiqui (DEN0001785009), Registered Dentist, General Registration. Dr Siddiqui’s registration can be verified free on the AHPRA public register at ahpra.gov.au. The full clinical team is listed by name.
Smile Solutions, Level 1, 220 Collins Street, Manchester Unity Building, Melbourne VIC 3000 — getting here. Phone 13 13 96, contact us, or theteam@smilesolutions.com.au. Monday–Friday 8.00am–6.00pm, Saturday 8.30am–1.30pm, Sunday by appointment. If a filling has broken and the tooth is painful, see emergency dentistry.
Published 21 October 2018. Lifespans are typical figures from research and clinical experience, not guarantees; outcomes vary between individuals. Findings quoted from the endodontic and cracked-tooth literature describe root-treated or cracked teeth and are included as evidence about sealing, isolation and cuspal coverage, not as figures for routine fillings. General information only; it does not replace advice from your treating practitioner.
Smile Solutions trades under ABN 28 193 514 103.
Images on This Page
-
https://www.facebook.com/tr?id=800557773428361&ev=PageView&noscript=1
(no alt text)
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/10/calendar_month.svg
(no alt text)
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/images/smile_solutions_logo_white.png
Smile Solutions Logo
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/images/smile_solutions_logo_purple.png
Smile Solutions Logo
-
https://www.smilesolutions.com.au/wp-content/uploads/2016/05/Maliha-150x150.jpg
Dr Maliha Siddiqui
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/09/CEREC-restorations-Smile-Solutions.png
CEREC Restoration Smile Solutions
-
https://www.smilesolutions.com.au/wp-content/uploads/2018/12/Dental-Filling-300x270.jpg
Dental Filling
-
https://www.smilesolutions.com.au/wp-content/uploads/2016/05/Peter-150x150.jpg
Dr Peter Henderson
-
https://www.smilesolutions.com.au/wp-content/uploads/2025/11/TMD-Teeth-Grinding-Smile-Solutions-300x270.png
Woman holding her face, looking concerned.
-
https://www.smilesolutions.com.au/wp-content/uploads/2017/03/get-chipped-tooth-fixed.jpg
get chipped tooth
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/images/family_owned_bussiness.png
Family Owned Business
-
https://www.smilesolutions.com.au/wp-content/themes/arcadian-wordpress-theme/assets/icons/icon--phone.svg
Smile Solutions Contact
-
https://www.facebook.com/tr? id=800557773428361&ev=PageView&noscript=1
(no alt text)